
Sean Lonergan, Cognitive Behavioural Psychotherapist in the Mood Disorders Service here in St Patrick’s Mental Health Services (SPMHS), explores depression.
Sean provides guidance on how best to understand the different ways depression can present and the best principles and practices that can guide treatment planning, including when to refer to specialist care.
What is depression?
As GPs in Ireland, you often provide the first opportunity for patients to be diagnosed with depression. You act as the primary, central point of access for mental health support, offering assessments, referrals and treatment plans for issues like anxiety and depression. GPs often provide the most enduring support for people living with depression.
Depression is more than normal sadness or stress response which affects mood, thinking, physical health and behaviour. The core symptoms of depression, according to the Diagnostic and Statistical Manual of Mental Disorders (DSM-5 (opens in a new tab)), must include depressed mood OR loss of interest/pleasure, plus three or four of the following:
- sleep disturbance
- appetite/weight change
- fatigue, low energy
- poor concentration
- feelings of guilt/worthlessness
- psychomotor change
- suicidal ideation.
Major depressive disorder requires symptoms to be persistent for more than two weeks with significant functional impairment. Symptoms cannot be caused by substances or better explained by another medical condition. Symptoms cause clinically significant distress or impairment in social, occupational, or other important areas of functioning.
Depression sub-types with specific presentations include:
- major depressive disorder
- persistent depressive disorder / dysthymia
- recurrent depression
- perinatal or postnatal depression
- depression with psychotic features
- bipolar depression (important to avoid misdiagnosis).
Supporting patients with depression is aided through careful assessment, seeking collateral information, establishing and maintaining links with referral and support services and providing education and support to patients and their families.
Approaching conversations about depression and low mood with patients
When trying to identify and diagnose depression in a busy GP clinic, it can help to slow down or, in the first 60 seconds, to try to observe and notice your patient’s presentation without assumption. It may be helpful to ask explicitly about low mood without judgement; to reassure about time if patients fear “burdening” their GP; and to respond with compassion and validation to aid rapport and trust-building.
Patient-centred communication is fostered by creating a safe disclosure environment through warmth, patience and empathy, signalling safety early; patients decide within seconds that they feel safe to disclose emotional distress.
It is important to ask about suicide risk directly and take immediate action if high risk of harm is identified, with an urgent referral or emergency department referral, and safety planning. Patients rarely offer this information voluntarily and helpful questions that you can ask may include checking if they have experienced any of the below over the past two weeks:
- thoughts of being better off dead
- thoughts of harming themselves
- any plan or preparation
- anything which stopped them from acting on thoughts/plans to end their life.
When assessing functional impact, which is an important severity marker of depression, it can help to ask about work performance, absenteeism, social withdrawal, and quality of relationships and self-care.
Challenges to diagnosing depression
There can be challenges to accurately diagnose depression as two‑thirds of patients may present to GPs with physical symptoms only, such as fatigue, sleep problems, headaches, chronic pain and gastrointestinal symptoms.
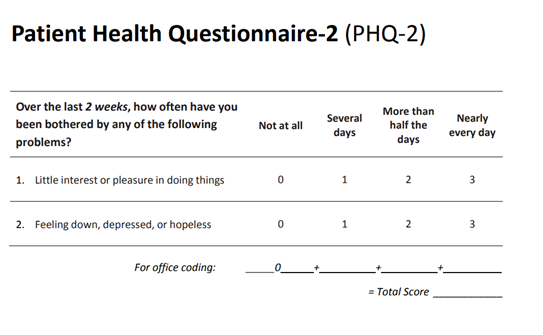
If you suspect your patient may be depressed, the two Patient Health Questionnaire-2 (PHQ2) questions outlined in the table below can help explore this. Ask your patient “over the past two weeks, how often have you been bothered by any of the following problems: feeling down, depressed or hopeless; and little interest or pleasure in doing things?”
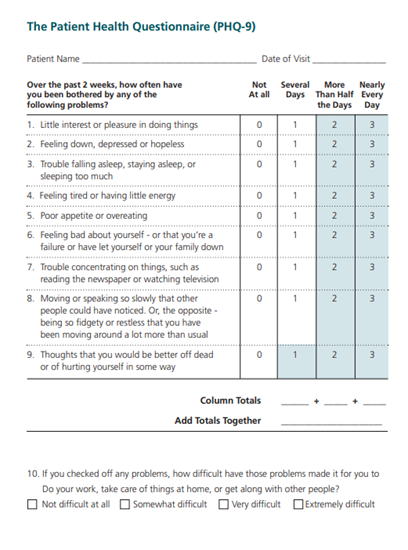
The PHQ-9 assessment scale (opens in a new tab) can also help clarify if patients’ symptoms may be related to depression.
Bipolar disorder and psychosis symptoms
If depression symptoms are identified, it is important to assess if your patient has experienced hypomania or mania symptoms in the past and/or psychosis symptoms.
Ante and postnatal depression
The World Health Organisation (WHO) describes a high prevalence of antenatal and postnatal depression (opens in a new tab) of between 10% and 13%. This makes early diagnosis and treatment a high priority for the wellbeing of the mother, child and family unit.
Specific, sensitively-asked questions can include:
- If the patient is having any difficulties caring for herself or the baby
- If the patient experiences any intrusive thoughts about harming herself or the baby.
These questions can help identify if depression may be present. If ante/postnatal depression is diagnosed, consider psychotherapy first. If prescribing medication, sertraline is preferred.
Depression in older adults
Older adults often present with more somatic symptoms, sleep disturbances and anxiety symptoms. Some 60% to 70% of people with dementia experience symptoms of depression and/or anxiety. Therefore, considering assessment of cognitive impairment versus depression using the Mini-Mental State Examination (opens in a new tab) (MMSE) may be indicated.
Depression, insomnia and sleep disorders
Sleep and depression have a strong bidirectional relationship. Insomnia doubles the risk of developing depression (opens in a new tab). Treating sleep disorders improves mood, functioning and relapse prevention.
Common sleep disorders to rule out include insomnia disorder, sleep apnoea, parasomnias and hypersomnia. If a specific sleep disorder is indicated, specialist referral pathways in Ireland include:
- sleep clinics (Beaumont Hospital, ResMed, PEI, Bon Secours, Mater Private)
- an eight-week Cognitive Behavioural Therapy (CBT) for Insomnia programme for psychological treatment of insomnia here in SPMHS, to which GPs can directly refer.
When to refer to specialist services
Follow the National Institute of Clinical Excellence (NICE) guidelines (opens in a new tab).
- Step 1: Assessment, referral, psychoeducation, monitoring and support.
- Step 2: Low-intensity therapy for mild depression.
- Step 3: Anti-depressants and high-intensity therapy for moderate to severe depression.
- Step 4: Specialist care for complex, high-risk, psychotic or treatment-resistant depression.
Referral options for GPs include to:
- a community mental health team
- primary care psychology (where available)
- counselling in primary care
- specialist perinatal mental health services
- private psychology or CBT therapists.
Urgent versus routine referrals
As a GP, you can make an urgent referral if there is:
- high suicide risk
- psychotic symptoms
- severe functional decline
- severe agitation or mania
- pregnancy/postnatal depression with moderate to severe symptoms.
You can make a routine referral if there is:
- treatment-resistant depression
- diagnostic uncertainty
- comorbid substance misuse.
If you identify treatment-resistant depression, which you might suspect when there has been no response after two adequate trials of anti-depressants, it may be helpful to consider:
- reassessing the diagnosis (for example, considering if it could be bipolar disorder or substance use)
- assessing what the therapeutic optimal dose for your patient is
- switching or augmenting the anti-depressant
- adding psychotherapy
- referring to specialist mental health services.
Day programmes and CBT
SPMHS provides a Depression Recovery Programme and Bipolar Recovery programme, as well as a range of other day programmes GPs can refer directly to. See more on our programmes here.
CBT can be also be accessed in SPMHS through our Dean Clinic outpatient services (four to six weeks to review for suitability).
There are also Health Service Executive (HSE) community mental health team CBT provisions, dependent on the county. The National Counselling Service (NCS) provides a Counselling in Primary Care (CIPC) service: learn more on the NCS and CIPC here (opens in a new tab).
The following websites list private accredited therapists:
- Cognitive Behavioural Psychotherapy Ireland (opens in a new tab)
- Irish Association for Counselling and Psychotherapy (opens in a new tab)
- Irish Association of Humanistic and Integrative Psychotherapy (opens in a new tab).
Other supports
- Aware support groups (opens in a new tab) (online and in-person)
- Pieta (opens in a new tab) (crisis support for suicide and self-harm)
- Mental Health Reform (opens in a new tab) (map of local services)
- Recovery College resources (opens in a new tab)
- HSE YourMentalHealth.ie (opens in a new tab) line (call 1800 111 888)
- Jigsaw (opens in a new tab) (for ages 12 to 25 yrs)
- Rotunda perinatal mental health supports (opens in a new tab)
- National Maternity Hospital perinatal mental health service (opens in a new tab).
Summary of recommendations
Depression is common and often presents somatically.
Making your consultation approach compassionate, open and sensitive to the needs of patients presenting with depression can help aid diagnosis and effective intervention.
The PHQ‑2 and PHQ‑9 scales are practical tools for aiding diagnosis and monitoring. It is important to match the treatment step to severity and treatment response; it is often helpful to combine medications and therapy for best outcomes.
Always assess suicide risk directly and be familiar with local and national referral options. Early intervention improves outcomes and reduces suicide risk.
Recommended treatments for mild depression include:
- monitoring symptoms
- behavioural activation (activity scheduling)
- guided self‑help (opens in a new tab)
- online CBT (such as SilverCloud)
- exercise programmes (opens in a new tab).
Recommended treatments for moderate depression include:
- prescribing an SSRI as first-line antidepressant (ADT)
- referring for CBT, interpersonal psychotherapy (IPT), or behavioural activation (BA)
- continuing lifestyle interventions
- reviewing in two to three weeks
- using PHQ‑9 to track improvement.
Recommended treatments for severe depression include:
- prescribing SSRI or Serotonin and Norepinephrine Reuptake Inhibitors (SNRIs)
- considering combination with therapy
- safety planning
- regular monitoring
- assessing for bipolar symptoms.